
A systematic-review thesis asks a different question from a standard empirical thesis: not “what did I find when I collected new data,” but “what does the existing evidence already say, and how rigorously was it found.” In Canadian nursing programs this format is increasingly accepted for a Major Research Paper, a thesis chapter, or occasionally the whole thesis itself — but “accepted” comes with conditions your supervisory committee will check line by line. Here is how the format actually works, step by step, and what turns a systematic review into an examiner-proof one.
What counts as a systematic-review thesis in nursing
A systematic review is not a longer literature review. It is a structured, reproducible method with a registered protocol, an explicit search strategy across named databases, documented inclusion and exclusion criteria, and a formal quality-appraisal step applied to every included study. The reporting standard nursing programs expect is PRISMA 2020 (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) — a 27-item checklist plus a flow diagram tracking records from identification through to the final included set. If your write-up cannot be checked against that checklist item by item, your committee will treat it as a narrative review with a systematic-sounding title, which is a common reason these theses come back for revision.
When your program will actually accept this format
Before you commit months to this design, confirm three things with your supervisor and your methodology chapter committee expectations, and your school of graduate studies:
- Whether a review counts as an acceptable thesis type at all. Some Canadian nursing graduate programs restrict the thesis to primary empirical research and only allow a systematic review as a Major Research Paper or a scoping-review variant instead.
- Whether you need a second reviewer. PRISMA-compliant screening and appraisal are normally done independently by two reviewers with a documented disagreement-resolution process. A one-person thesis review has to state clearly how this requirement was met or substituted, and your committee will ask.
- Whether your topic already has a recent Cochrane or JBI review. If one was published in the last two to three years covering the same population, intervention and outcomes, your committee will expect you to either update it, narrow the question, or justify why a fresh review is still warranted.
Systematic review, scoping review, or integrative review: which one is your thesis actually doing
Students often propose “a systematic review” when the question they are really asking calls for a different design, and committees catch this early. The three are not interchangeable:
- Systematic review answers a narrow, well-defined question (often effectiveness of an intervention) and includes a formal quality-appraisal and risk-of-bias step for every study. This is the design examiners expect when a numeric outcome — glycaemic control, pain scores, readmission rates — is being compared across studies.
- Scoping review maps the breadth of evidence on a broader question (“what is known about X”) without appraising study quality in the same formal way. It follows the PRISMA-ScR extension rather than PRISMA 2020, and is often the better fit when the literature is too heterogeneous in design for a systematic review, or when the goal is to identify gaps rather than pool an effect.
- Integrative review deliberately combines experimental and non-experimental evidence, including qualitative studies, within one synthesis — common in nursing because so many practice questions have both quantitative outcome data and qualitative patient-experience data that a strict systematic review format cannot combine cleanly.
Name the correct one in your title and proposal from the start. A thesis titled “a systematic review” that turns out to be scoping in method is one of the fastest ways to trigger a proposal-stage revision request.
The eight steps, in order
- Formulate a PICO (or PICOS/PEO) question. Population, Intervention, Comparison, Outcome — for example: in adult patients with type 2 diabetes (P), does a nurse-led self-management education programme (I), compared with usual care (C), improve glycated haemoglobin at six months (O)? A vague question is the single most common reason a review’s search strategy fails.
- Register the protocol before you search. PROSPERO, the international prospective register of systematic review protocols hosted by the University of York’s Centre for Reviews and Dissemination, is free to register on and is what most Canadian nursing committees will ask for as proof your question and methods were fixed in advance, not adjusted after seeing the results. Registration also prevents duplicate reviews on the same question.
- Build the search strategy across the field’s real databases. For nursing this normally means, at minimum, CINAHL (Cumulative Index to Nursing and Allied Health Literature, published by EBSCO and the field’s dedicated index) and the Cochrane Library (owned by Cochrane, published by Wiley, home of the Cochrane Database of Systematic Reviews), plus MEDLINE/PubMed and Embase where your library provides access. JBI (formerly the Joanna Briggs Institute) also publishes its own evidence-synthesis database and a widely used systematic-review methodology that some Canadian schools of nursing formally teach instead of, or alongside, the Cochrane approach — check which one your program’s research methods course used, since your committee will expect that vocabulary.
- Screen in two stages, by two reviewers where possible. Title/abstract screening first, then full-text screening against your pre-set inclusion and exclusion criteria. Record every excluded full-text study and the specific reason it was excluded — this list becomes an appendix and examiners check it.
- Appraise the quality of every included study. Use a named, published tool matched to each study design — the JBI Critical Appraisal Checklists (separate tools exist for RCTs, cohort studies, qualitative studies and more) or the Cochrane Risk of Bias 2 (RoB 2) tool for randomized trials are the two most defensible choices in a nursing thesis. Report the appraisal score or risk-of-bias judgement for each study in a table; do not just state that “quality was assessed.”
- Extract and synthesize the data. Build a structured extraction table (author, year, country, design, sample, intervention, outcome measures, key findings) before you start writing prose. If study designs and outcome measures are too heterogeneous for meta-analysis — common in nursing reviews mixing quantitative and qualitative evidence — use a structured narrative synthesis and say so explicitly rather than forcing numbers that do not belong together.
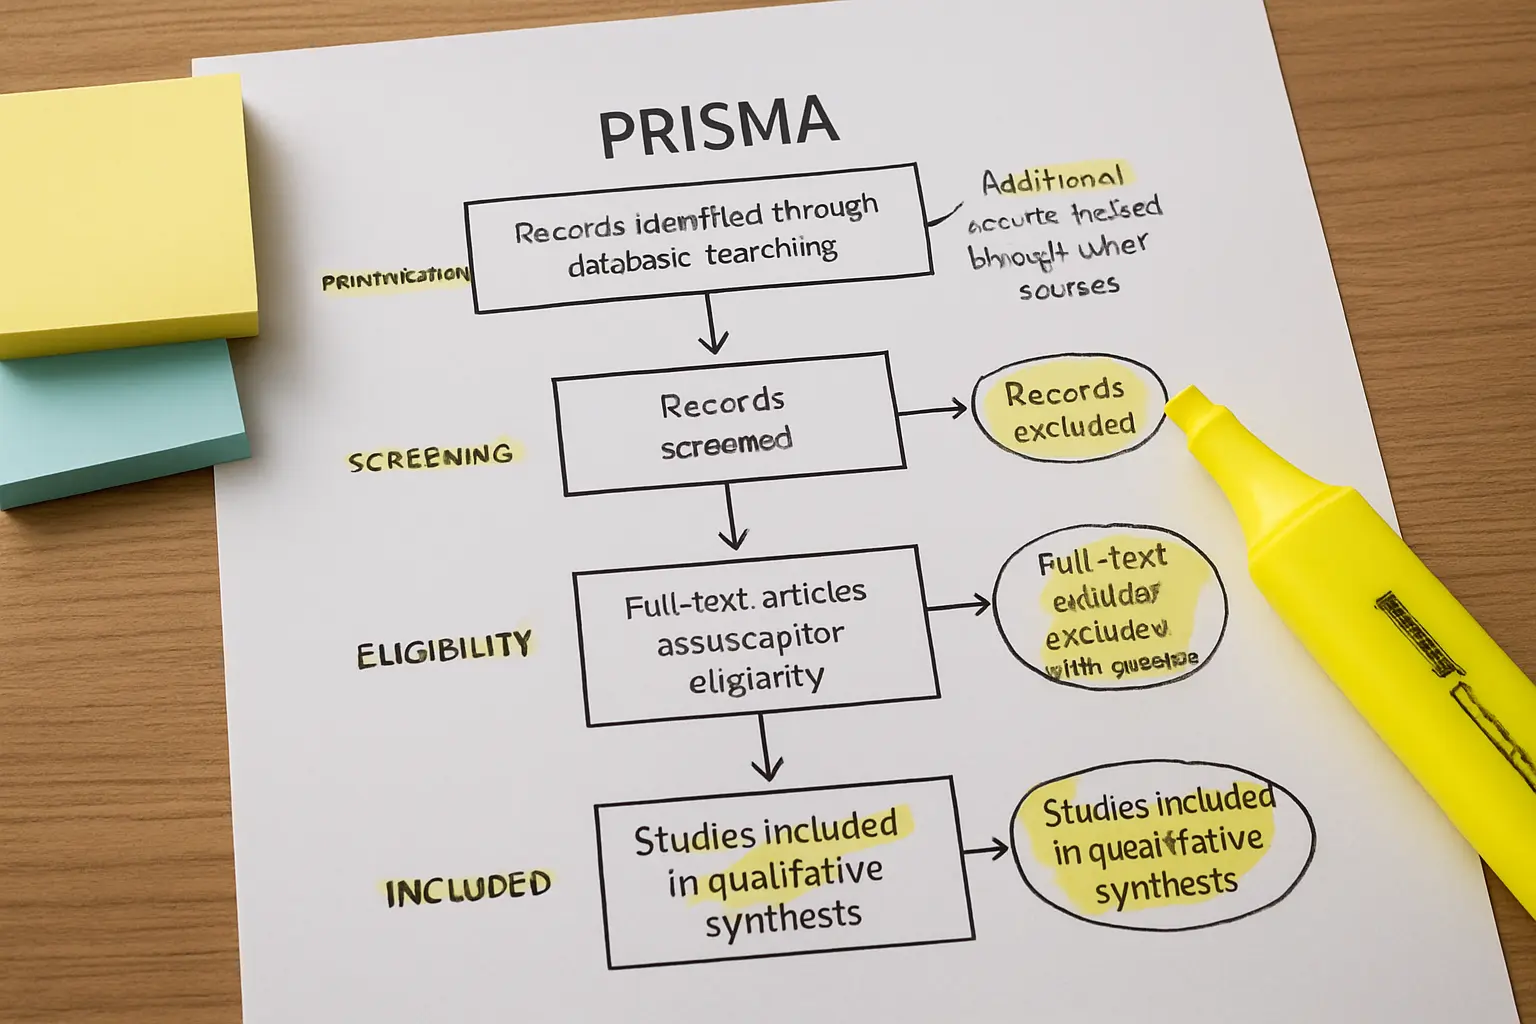
- Produce the PRISMA flow diagram. Records identified through each database, duplicates removed, records screened, records excluded with reasons, full-text articles assessed, and studies finally included. This diagram is usually the single most-checked figure in the entire thesis defence.
- Write the discussion against the PRISMA checklist, not just against your findings. State the certainty of the evidence, the review’s limitations (search language restrictions, publication bias, heterogeneity), and what a future primary study in this area should actually measure. A results section without a stated evidence-certainty judgement (GRADE, or a plain-language equivalent) reads as incomplete to most nursing examiners.
Building the actual search string

A search strategy that a librarian or examiner cannot reproduce from your methods chapter is a common weak point. For each database, document the exact combination of subject headings and free-text terms, not just the keywords you typed into a box:
- Start from your PICO concepts and translate each one into that database’s controlled vocabulary — CINAHL Subject Headings for CINAHL, MeSH terms for MEDLINE/PubMed, Emtree for Embase. The same concept often has a different official heading in each.
- Combine synonyms and the controlled-vocabulary term with OR within each concept (“nurse-led” OR “nurse practitioner” OR “advanced practice nursing”), then combine the concept groups with AND.
- Apply filters deliberately and report them — publication date range, language, study design filter — and state the justification for each in the methods chapter, since an unexplained filter is read as narrowing the search to get a manageable number of hits rather than for a methodological reason.
- Search grey literature and practice-guideline sources relevant to nursing specifically, such as the Registered Nurses’ Association of Ontario (RNAO) Best Practice Guidelines repository, in addition to the academic databases, and record that you did.
- Save the complete search string for every database as a supplementary file or appendix — reviewers and examiners increasingly expect this to be reproducible, not just described in prose.
A worked example of the protocol paragraph
Committees respond well to a protocol paragraph that states the method plainly before any findings appear. A usable template:
“This review followed PRISMA 2020 reporting guidance and was registered prospectively on PROSPERO (registration number pending at protocol stage). Searches were conducted in CINAHL, MEDLINE, and the Cochrane Central Register of Controlled Trials from database inception to [month, year], with no language restriction. Two reviewers independently screened titles, abstracts, and full texts; disagreements were resolved by discussion with a third reviewer where consensus was not reached. Risk of bias in included randomized trials was assessed using the Cochrane RoB 2 tool.” Adjust the specifics to your real protocol, but keep the structure — method, registration, databases, dual review, appraisal tool — in that order.
What a defence looks like for this thesis type
Examiners on a systematic-review thesis tend to focus their questions differently than for an empirical thesis. Expect to be asked, specifically:
- Why you chose the databases you searched and what you might have missed by not searching others (Scopus, Web of Science, dissertation databases for grey literature).
- To defend one specific inclusion or exclusion decision from your PRISMA flow diagram, usually a borderline study you excluded.
- How you would update the review a year from now — is the search strategy saved and rerunnable, and would you re-register the update on PROSPERO or amend the existing record.
- Whether your synthesis conclusions are proportionate to the number and quality of studies included, not overstated relative to a small or low-certainty evidence base.
Prepare a one-page summary of your PRISMA flow-diagram numbers and your appraisal-tool scores before the defence — most students who stumble on these questions had the numbers in the thesis but not memorized for the room.
Where these theses lose marks
- Calling it “systematic” while searching only one database or skipping grey literature without justifying the decision.
- Reporting a quality-appraisal step in the methods chapter but never showing appraisal results per study.
- A PRISMA diagram whose numbers do not reconcile — screened, excluded and included counts must add up.
- Conclusions that go beyond what a small number of low-quality included studies can actually support.
Frequently asked questions
Is a systematic review considered “original research” for a nursing thesis?
Yes, when it follows a registered protocol and a documented, reproducible method — the methodology itself, and the synthesis of a body of evidence no one had assembled that way before, is the original contribution. Confirm this framing explicitly with your supervisor before you propose it.
Do I need ethics board approval for a systematic review?
Usually not, since you are working with already-published data rather than human participants directly, but some Canadian research ethics boards still want a short exemption letter on file. Ask your REB office rather than assuming.
How many studies is “enough” for a nursing systematic review thesis?
There is no fixed minimum. Committees look at whether your search was comprehensive and your inclusion criteria defensible, not at a target study count — a well-run review with eight included studies is stronger than a loosely run one with thirty.
Can I combine a systematic review with a small primary study in the same thesis?
Some programs allow a two-part or manuscript-style (article-based) thesis combining a systematic review chapter with an empirical chapter. Confirm with your school of graduate studies whether this structure is permitted before you plan around it.
What software do reviewers actually use to manage screening?
Covidence and Rayyan are the two tools most commonly used for title/abstract and full-text screening in nursing systematic reviews; both let two reviewers screen independently and flag conflicts automatically. If your review question is closer to “what does the qualitative evidence say” than “what does the trial evidence say,” the same eight-step process applies but your appraisal tool changes — see how the field also handles instrument selection in choosing a nursing scale for a related, instrument-focused decision.
Where Tesify fits
None of the eight steps above can be outsourced to a generic AI writer — the protocol, the database searches and the appraisal judgements have to be yours. What Tesify speeds up is the drafting and formatting layer around that real work: turning your extraction table into clean synthesis prose, keeping PRISMA-section headings consistent, and generating a properly formatted reference list as you go, so the months you spend on the review itself are not lost to reformatting the week before submission.